Naloxone 4 mg vs. 8 mg: What the CDC Study Found

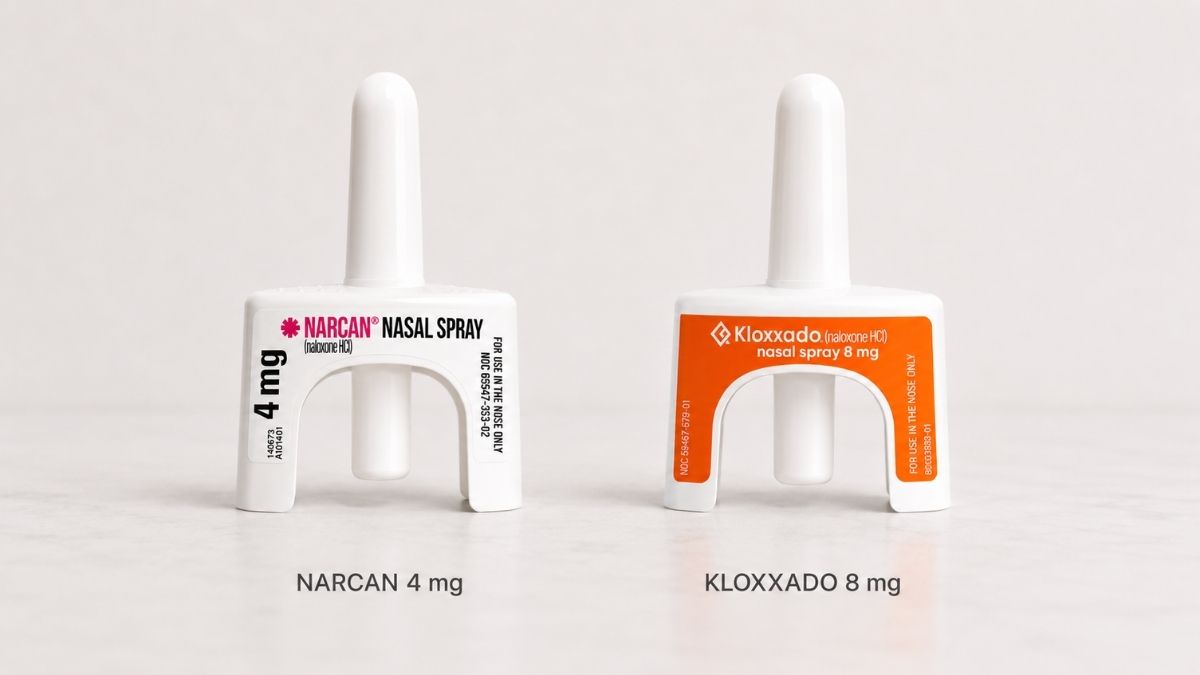
If you are carrying naloxone for a family member, friend, client, student or someone in your community, seeing two different strengths can raise a reasonable question: If one nasal spray contains 4 mg of naloxone and another contains 8 mg, is the higher dose better?
The answer is not as simple as “more is better.”
A real-world study published by the Centers for Disease Control and Prevention compared 4 mg and 8 mg intranasal naloxone used by New York State Police during suspected opioid overdoses. Researchers found no statistically significant difference in survival or in the average number of naloxone doses administered. They did, however, find that opioid-withdrawal signs and symptoms were reported more often among people who received the 8 mg product. Read the CDC’s 4 mg vs. 8 mg naloxone study
That finding is useful when comparing naloxone products. But it should never create hesitation during an overdose.
If someone may be experiencing an opioid overdose, use the naloxone you have. Do not delay giving an 8 mg product because you are looking for a 4 mg dose. The immediate priority is restoring breathing and getting emergency help.
What do 4 mg and 8 mg naloxone actually mean?
Naloxone is a medication that can temporarily reverse the effects of opioids. During an opioid overdose, those effects can include dangerously slow, shallow or stopped breathing. Naloxone works by blocking opioid effects at opioid receptors, allowing breathing to improve when opioids are causing the respiratory depression.
With intranasal naloxone, the medication is delivered as a spray into the nose.
A product labeled 4 mg delivers 4 milligrams of naloxone in one single-use spray. An 8 mg product contains a higher amount of naloxone in each spray.
That does not mean an 8 mg product should automatically be thought of as “twice as effective.” The number tells you the labeled amount of naloxone in the product; it does not tell you how much additional benefit that amount will necessarily provide during a particular overdose.
The more useful question is what happened when these different strengths were used in actual overdose responses.

What did the CDC study compare?
From March 2022 through August 2023, the New York State Department of Health worked with New York State Police to compare the use of 4 mg and 8 mg intranasal naloxone during suspected opioid overdoses.
Three of the state’s 11 police troops received the 8 mg product. The remaining troops continued using 4 mg naloxone.
After reviewing the reports, researchers included 354 suspected opioid-overdose responses in the analysis:
101 people received 8 mg intranasal naloxone
253 people received 4 mg intranasal naloxone
This was a real-world field comparison rather than a randomized clinical trial. The information came from law-enforcement responders treating suspected opioid overdoses in the field.
That distinction matters. The study tells us what researchers observed in these responses. It does not establish that one dose will produce the same result in every person, every community or every overdose situation.
Did 8 mg naloxone work better than 4 mg?
The researchers looked at several outcomes, including survival, how many naloxone doses were administered and signs or symptoms that appeared after naloxone was given.
The main results were:
| Outcome | 8 mg naloxone | 4 mg naloxone |
|---|---|---|
| Survival | 99.0% | 99.2% |
| Average number of doses administered | 1.58 | 1.67 |
| Opioid-withdrawal signs or symptoms, including vomiting | 37.6% | 19.4% |
There was no statistically significant difference in survival between the two groups.
Researchers also found no statistically significant difference in the average number of naloxone doses administered. People in the 8 mg group received an average of 1.58 doses, compared with 1.67 doses among people in the 4 mg group.
The important difference appeared in reported withdrawal signs and symptoms.
Opioid-withdrawal signs and symptoms, including vomiting, were reported in 37.6% of people who received 8 mg, compared with 19.4% of those who received 4 mg.
The CDC reported that people in the 8 mg group had 2.51 times the risk of the combined withdrawal-sign-and-symptom outcome compared with the 4 mg group.
In this particular field study, researchers therefore did not identify a survival advantage or a reduction in the average number of administered doses with 8 mg, while opioid-withdrawal signs and symptoms were reported significantly more often.
That is different from saying the two products are identical—or that an 8 mg product should never be used.
Why can naloxone cause opioid withdrawal?
Naloxone rapidly blocks the effects of opioids.
If someone is physically dependent on opioids, that rapid reversal can trigger precipitated withdrawal—withdrawal that begins abruptly after an opioid antagonist such as naloxone displaces or blocks opioid effects.
Withdrawal after naloxone can include symptoms such as nausea, vomiting, sweating, anxiety or irritability, rapid heart rate, aches and tremors.
The CDC explains that naloxone may cause withdrawal symptoms in someone who is physically dependent on opioids, but those effects must be considered alongside the much more immediate danger of an untreated overdose. See the CDC’s Naloxone Frequently Asked Questions
During an opioid overdose, slowed or stopped breathing can be fatal. Naloxone is being given because reversing those opioid effects is urgent.
The New York study found an association between the 8 mg product and a higher prevalence of reported opioid-withdrawal signs and symptoms. It does not show that every person receiving 8 mg will experience severe withdrawal.
There is also an important detail about vomiting.
Vomiting was part of the larger category of withdrawal signs and symptoms. When researchers examined vomiting by itself, it occurred in 20.8% of the 8 mg group and 13.8% of the 4 mg group. That difference was not statistically significant.
So it would be inaccurate to say that the study proved 8 mg naloxone caused significantly more vomiting. The significant difference was in the broader category of opioid-withdrawal signs and symptoms, including vomiting.
Does this mean 8 mg naloxone should not be used?
No.
This is one of the most important points to take away from the research.
If you are with someone who may be experiencing an opioid overdose and the naloxone available to you is an 8 mg nasal spray, use it.
Do not wait to find a 4 mg product. Do not spend valuable time comparing the number on the package while the person’s breathing is dangerously slow or absent.
The CDC recommends giving naloxone when an opioid overdose is suspected and seeking emergency medical assistance. Naloxone can begin restoring breathing within a few minutes when opioids are causing respiratory depression. See the CDC’s guidance on responding to a suspected overdose
The study is more useful for a different question: when public-health programs, community organizations and other groups are deciding which naloxone products to carry, does existing evidence show that the higher-dose product produces better real-world outcomes?
In this New York field comparison, researchers did not identify that additional benefit.
That is not a reason to withhold 8 mg naloxone during an emergency.
What does the study not tell us?
The results are useful, but they have limitations.
The study involved New York State Police responses in one state. The drug supply and overdose circumstances can differ from one community to another.
Only 101 of the 354 included cases involved the 8 mg product because only three of the 11 police troops received that formulation.
Researchers also did not have comparable information about exactly which substance each person had used, the amount used, their vital signs or other characteristics that might have influenced their response.
The post-naloxone symptoms were documented by law-enforcement personnel rather than medical clinicians. The researchers acknowledged that symptoms and behaviors might therefore have been classified inconsistently.
For those reasons, the study should not be interpreted as proof that one naloxone strength will produce the same result in every overdose.
The CDC’s conclusion was measured: the field comparison identified no benefit from administration of the 8 mg product compared with the 4 mg product, while additional data are needed to determine whether higher-dose intranasal naloxone provides benefits in other community settings.
What about fentanyl? Doesn't a stronger opioid require stronger naloxone?
This is one reason people may assume that 8 mg naloxone must be preferable.
Fentanyl and other potent synthetic opioids can cause severe respiratory depression, and some overdose responses require more than one dose of naloxone.
But the possibility of needing additional naloxone does not establish that everyone experiencing an overdose should receive an 8 mg product as the first dose.
The CDC researchers specifically considered their findings in the context of the increased prevalence of synthetic opioids, including fentanyl, in the drug supply. Even in that environment, they found no statistically significant difference in survival or in the average number of naloxone doses administered between the 4 mg and 8 mg groups.
That does not mean 4 mg will always be enough.
It means the evidence from this study does not support a simple rule that a larger number on the naloxone package automatically produces a better overdose outcome.
If the first dose does not restore normal breathing, the response continues. That is why carrying more than one dose of naloxone and getting emergency medical assistance remain important.
What should you do during a suspected opioid overdose?
When someone is unresponsive and an opioid overdose may be involved, the immediate goal is not determining the ideal naloxone strength. It is responding quickly.
Give the naloxone available and call 911.
The CDC advises starting with one dose of naloxone. If the person does not respond adequately after approximately two to three minutes, another dose may be given. Read the CDC’s current naloxone guidance
If the person is unresponsive and is not breathing normally, provide appropriate resuscitation according to your training or emergency-dispatch instructions. Current American Heart Association guidance emphasizes that naloxone administration should occur alongside—not delay—appropriate resuscitation and activation of emergency medical services. See the American Heart Association’s current opioid-overdose resuscitation guidance
Stay with the person until emergency help arrives.
Even if the person wakes up after naloxone, the emergency is not necessarily over. Naloxone’s effects can wear off while opioids remain in the body, so continued observation and emergency medical evaluation remain important.
If you want practical instruction before an emergency happens, The Robin Foundation provides naloxone and overdose-prevention training for individuals, families, schools, organizations and communities.
Can I get naloxone before I need it?
Yes, and carrying naloxone before an emergency occurs is far better than trying to find it during one.
The Robin Foundation provides access to free NARCAN for eligible Florida residents through its community overdose-prevention work.
If you or someone you care about may be at risk of experiencing or witnessing an opioid overdose, you can request free naloxone from The Robin Foundation.
The Foundation’s overdose-prevention resources also include information about finding naloxone in Florida and locating naloxone resources in other states.
Being prepared does not mean you expect an overdose to happen. It means you have a tool available if one does.
The takeaway on 4 mg vs. 8 mg naloxone
The best way to understand this evidence is to separate product comparison from emergency response.
When researchers compared 4 mg and 8 mg intranasal naloxone in 354 suspected opioid-overdose responses handled by New York State Police, they found no statistically significant difference in survival or in the average number of doses administered. Opioid-withdrawal signs and symptoms were reported significantly more often among people who received the 8 mg product.
Those findings can help inform conversations about naloxone products.
But during an actual suspected overdose, the priority is simpler:
Use the naloxone you have. Call 911. Support the person’s breathing according to your training or dispatcher instructions, and give another dose if needed.
A discussion about naloxone strength should help people make informed decisions. It should never become a reason to delay an emergency response.
Be prepared before an overdose happens
You do not have to wait until an emergency to learn what to do.
The Robin Foundation works to expand naloxone access and provide overdose-prevention education so families, schools, workplaces and communities are better prepared to recognize and respond to suspected opioid overdoses.
Request free naloxone or learn about The Robin Foundation’s naloxone training.
This article is for educational purposes and is not individualized medical advice. Follow the instructions provided with the naloxone product you carry and current emergency medical guidance.
Related Posts
Naloxone 4 mg vs. 8 mg: Is a Higher Dose Better?